NABH dashboards
ALOS, infection rates, medication errors, audit-ready
IPD, OPD, OT, lab, pharmacy, HR, NABH-ready dashboards. A small-hospital implementation that runs in 60 days, not 12 months. Built around the way East-India hospitals procure, deploy, and report.
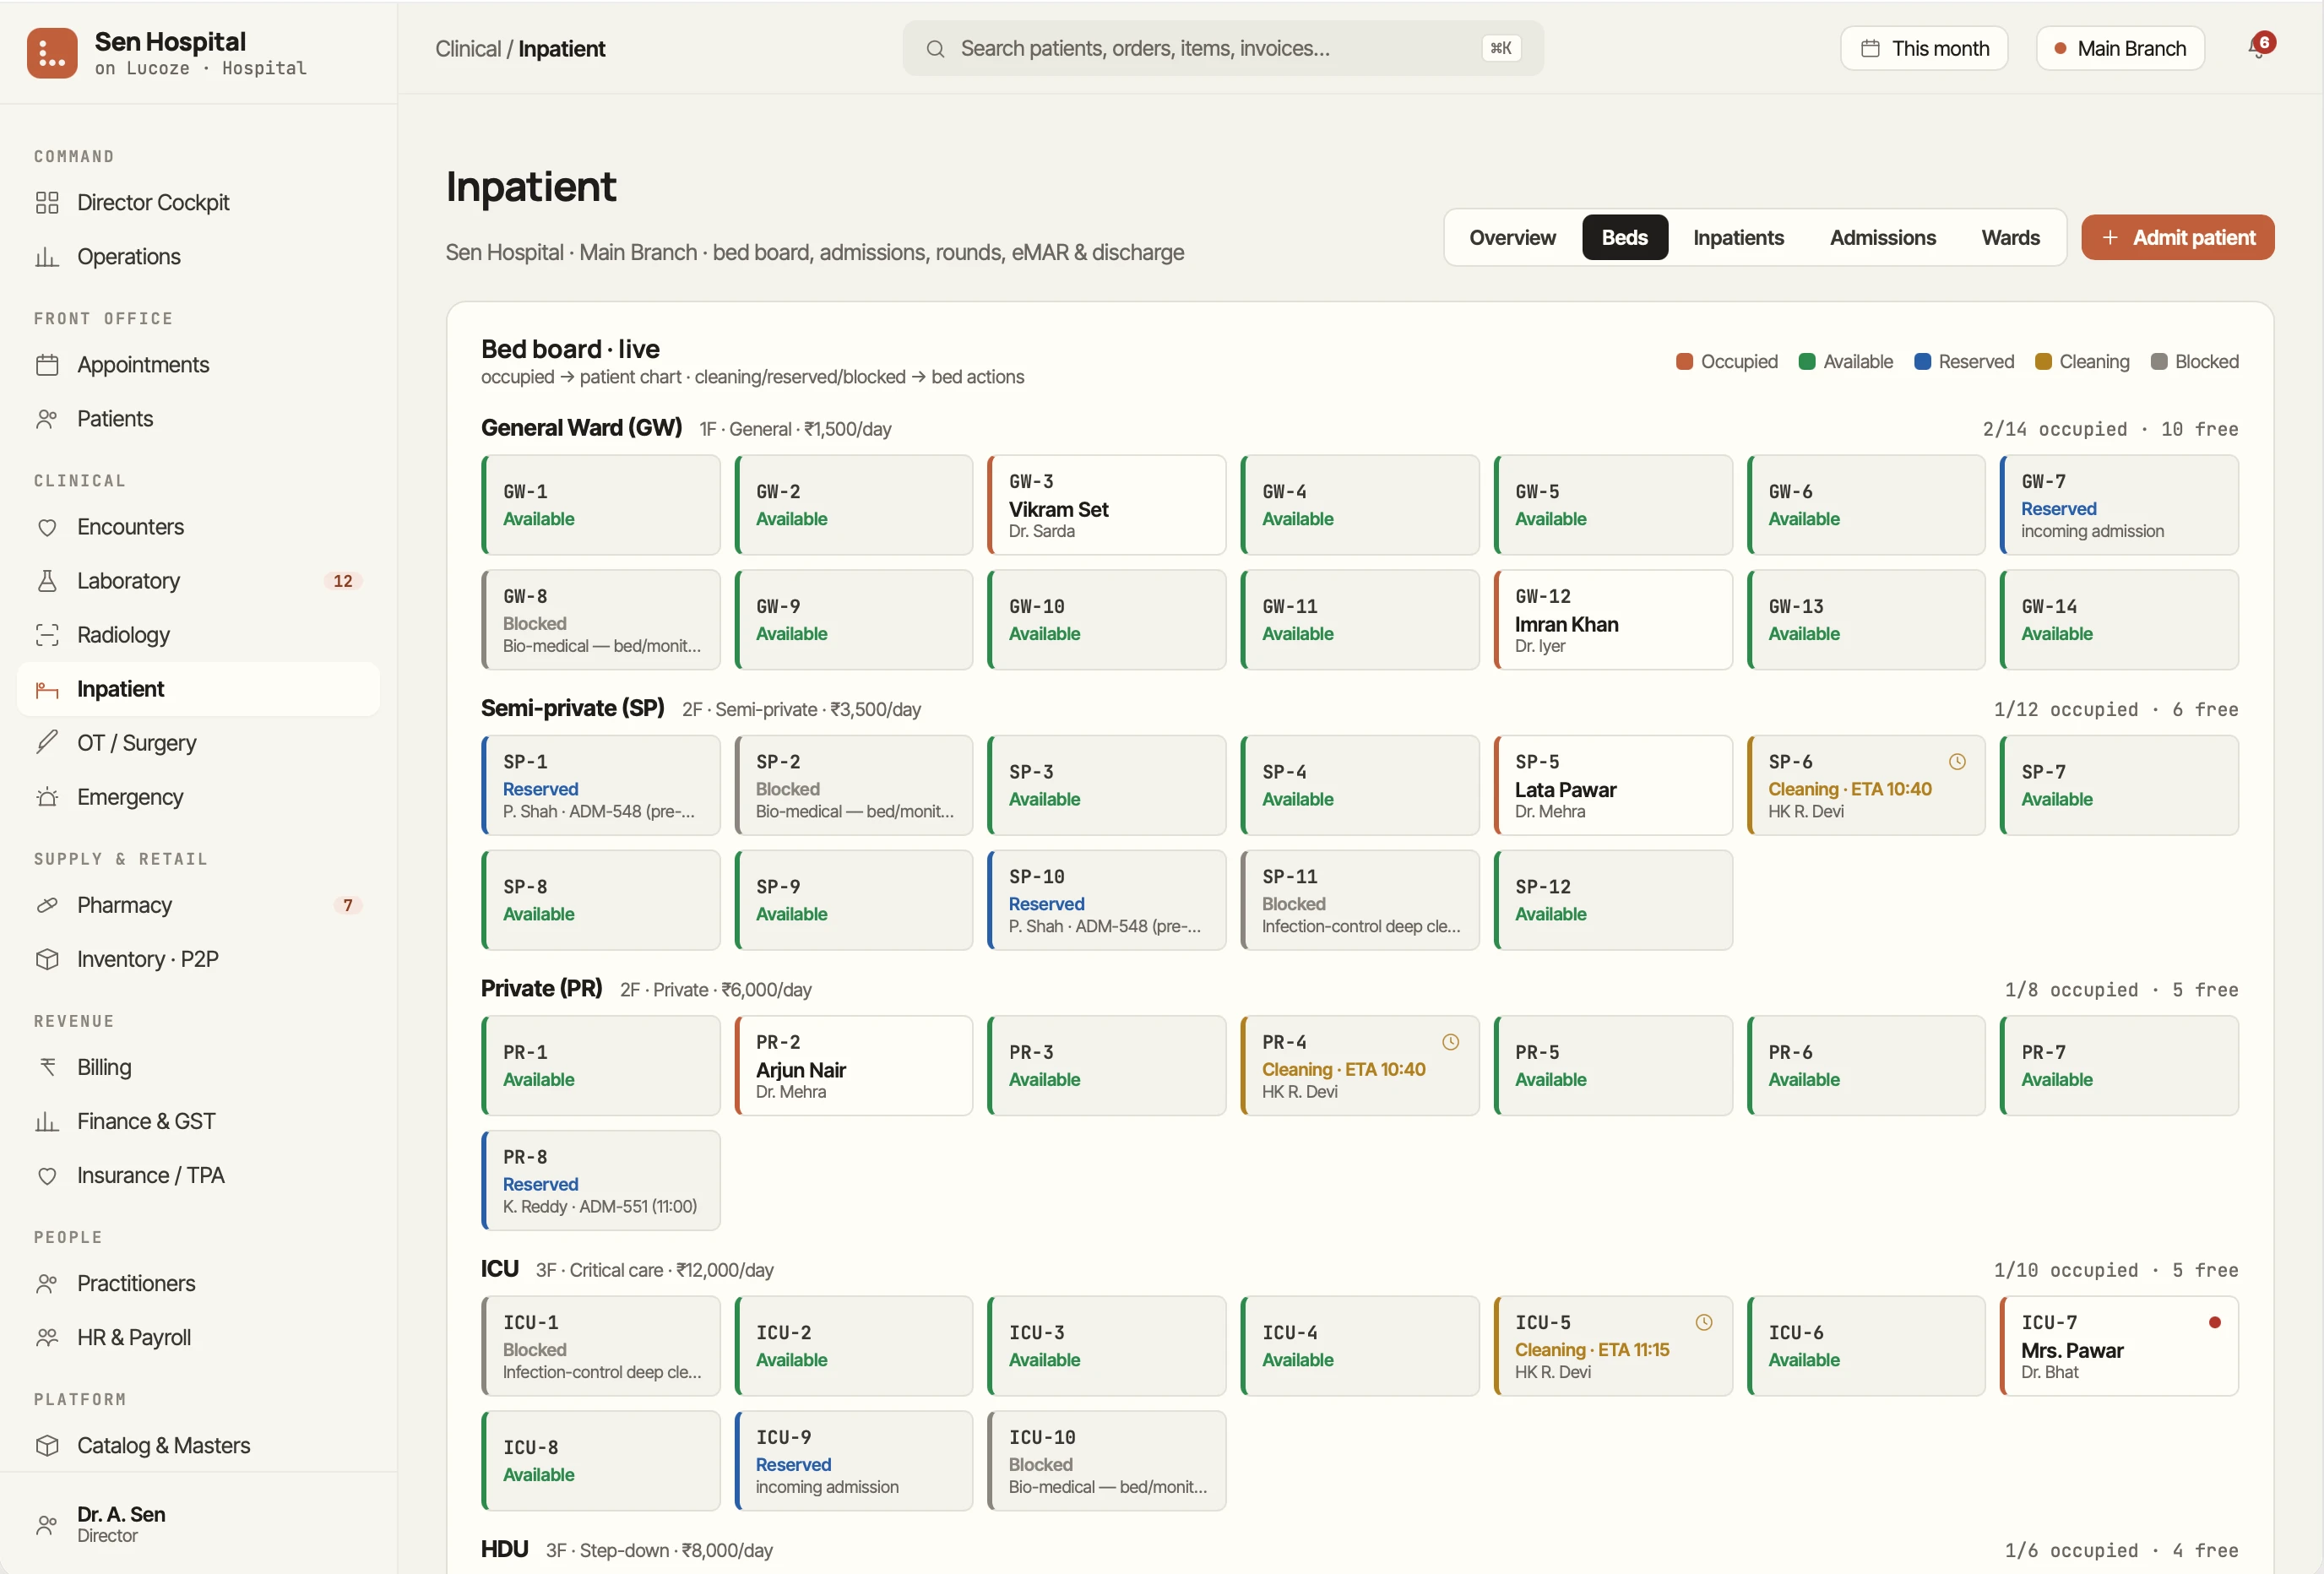
Tap any module to step through a few real screens.
Hospitals rarely switch for a nicer screen. They switch because the rules changed and the old system did not keep up. These are the ones a 20-100 bed hospital meets this year.
An example, not a customer story: a 50-bed multispecialty hospital with OPD, IPD, an OT, an in-house pharmacy and a lab, already running an older hospital system.
The current system stays live. We import the patient master, rate cards, formulary and current stock, with no migration fee.
Often the pharmacy. Since 22 September 2025 most medicines are taxed at 5% instead of 12%, and some at nil. The rate follows each medicine's HSN code, so a counter billing one flat rate is wrong on part of the shelf. Fix that first, prove it, then expand.
Around days 15 to 30, OPD goes live on Lucoze while IPD shadows it. Compare the two systems' daily totals until they agree, and move on only when they do.
Three separate registrations: the facility on HFR, each doctor on HPR, and an ABHA created or linked at the front desk for each patient. We walk your team through all three, because software alone does not register you.
IPD, OT, pharmacy and lab move one at a time, and the old system becomes read-only around day 45. HR, payroll and the NABH reports close the 60 days. You can export all your data at any time: being free to leave is what makes it safe to join.
Most small hospitals run on 3-7 separate tools. Lucoze brings the hospital side into one place, so your administrator stops being the link between them, and leaves your accounts where they are.
All modules included. Implementation manager for 60 days. Dedicated CSM thereafter. See pricing →
30-minute call. We bring our medical director, you bring yours. No pitch deck.